
Abstract
Autism spectrum disorder (ASD) is characterised by the concomitant occurrence of impaired social interaction; restricted, perseverative and stereotypical behaviour; and abnormal communication skills. Recent epidemiological studies have reported a dramatic increase in the prevalence of ASD with as many as 1 in every 59 children being diagnosed with ASD. The fact that ASD appears to be principally genetically driven, and may be reversible postnatally, has raised the exciting possibility of using gene therapy as a disease-modifying treatment. Such therapies have already started to seriously impact on human disease and particularly monogenic disorders (e.g. metachromatic leukodystrophy, SMA type 1). In regard to ASD, technical advances in both our capacity to model the disorder in animals and also our ability to deliver genes to the central nervous system (CNS) have led to the first preclinical studies in monogenic ASD, involving both gene replacement and silencing. Furthermore, our increasing awareness and understanding of common dysregulated pathways in ASD have broadened gene therapy’s potential scope to include various polygenic ASDs. As this review highlights, despite a number of outstanding challenges, gene therapy has excellent potential to address cognitive dysfunction in ASD.
Background
“Between stimulus and response there is a space. In that space is our power to choose our response. In our response lies our growth and our freedom”—Viktor E Frankl.
In autism spectrum disorder (ASD), a neurodevelopmental disorder affecting ~ 1.5% of the population, aetiologically diverse deficits in cognitive plasticity lead to broad impairments in communication and restricted, repetitive behaviours. Comorbidities are common (~ 70% of cases) and include epilepsy; attention, mood and language disorders; sleep disturbance; gastrointestinal problems; and intellectual disability.
Despite the great personal and sociological cost of ASD (estimated to be $2 million/patient/year), only the antipsychotics risperidone and aripiprazole are currently FDA-approved to treat ASD, indicated solely in the treatment of irritability symptoms. A fundamental reason for this lack of disease-modifying therapies may relate to ASD’s pathogenesis, which appears to be principally driven by heterogeneous genetic mutations and variants and modulated by diverse gene × environment interactions, to include pregnancy-related factors (e.g. maternal immune activation, maternal toxins) and perinatal trauma. Many of the encoded proteins implicated in ASD pathogenesis—such as cytoskeletal proteins, cell adhesion molecules and DNA-binding proteins—may be ‘undruggable’ using conventional small molecule drugs, which principally only modulate the function of receptors and enzymes.
In contrast, gene therapy—broadly defined as the delivery of nucleic acid polymers into cells to treat disease—may be used to repair, replace, augment or silence essentially any gene of interest in a target cell, opening up new areas of the proteome for drug targeting. Other advantages of gene therapy versus small molecules include the ability to effect long-lasting clinical benefit with a single treatment and the potential to control cellular targeting via vector modifications.
Indeed, gene therapy is already making a clinical impact in the field of neurology, with Nusinersen, an antisense oligonucleotide therapy approved in Spinal muscular atrophy (SMA), and more recently Luxturna, a viral-based gene replacement strategy approved in Leber’s congenital amaurosis, acting as the first disease-modifying therapies in both of these diseases. In addition, a clinical trial in SMA by AveXis using systemic delivery of recombinant adeno-associated virus 9 (rAAV9) carrying a replacement SMN1 gene recently proved safe and efficacious in neonates. On the other hand, gene therapies are clearly expensive in the short-term, with current therapies costing at least $500,000 per treatment, and thus remaining unaffordable in many healthcare systems (see ref for a thorough economic analysis).
This review will highlight key targets for ASD gene therapy, the utility of ASD models, and recent advances in our ability to deliver such therapies to the central nervous system (CNS). It will then move on to discuss recent gene therapy strategies in ASD, concentrating on conditions with available preclinical data, and the roadblocks facing their clinical translation.
Genetic targets in ASD
| Monogenic ASD | Mutated gene | Chromosome | Protein function | Autism prevalence | Other characteristics |
|---|---|---|---|---|---|
| Fragile X syndrome | FMR1 (encodes FMRP) | X | Binds and transports specific mRNAs from the nucleus to the ribosome | ~ 30% | Long/narrow face, macroorchidism, long ears and philtrum, mild to moderate intellectual disability, hyperactivity, intellectual disability (ID), seizures |
| Rett syndrome | MECP2 | X | Chromatin modification | ~ 60% | Microcephaly, breathing irregularities, language deficits, repetitive/stereotyped hand movements, epilepsy, ID |
| MECP2 duplication syndrome | MECP2 | X | Chromatin modification | ~ 100% | Brachycephaly, spasticity, recurrent respiratory infections, gastrointestinal hypermotility, genitourinary abnormalities, epilepsy, ID |
| Tuberous sclerosis | TSC1TSC2 | 916 | Inhibition of translation via mTORC1 inhibition | ~ 50% | Benign tumours in multiple organs, epilepsy |
| Angelman syndrome | UBE3A | 15 | Targeting of proteins for destruction via ubiquitin-tagging | ~ 30% | Cheerful demeanour, microcephaly, epilepsy, speech deficits, sleep disturbance, epilepsy, ID |
However, in such a heterogeneous condition as ASD, it is important not to become evangelical about a single causative mechanism, especially given recent insights into the apparently critical roles of immune dysfunction and epigenetics in at least certain ASD cases. Furthermore, recent phase II clinical trials which looked to regulate synaptic function via GABA and glutamate receptor modulation failed to demonstrate significant overall benefit, despite strongly positive responses in certain patients. Thus, it is important to consider whether targeting the synapse using gene therapy may be most appropriate for correcting particular ASD endophenotypes in specific patient subsets, rather than seeing it as a panacea for ASD, a topic that is returned to later in this article.
Modelling ASD in rodents: a platform for proof-of-principle studies
The field of gene therapy is littered with examples of therapies which failed to translate from their preclinical promise. In many cases, blame can be attributed to the predictive validity of the animal model used, which is itself related to its construct validity (i.e. how well the model mimics disease aetiology) and face validity (i.e. how closely the model’s phenotype represents the human disorder).
Given the challenges clinicians have faced in developing diagnostic criteria for ASD, and how various social traits often appear to be inherently ‘human’ qualities (although this is itself highly contested), it is little wonder that generating ASD animal models with good face validity has been challenging. Nevertheless, whilst caution should always be taken when ascribing behavioural outcomes in animals to autism, various monogenic ASD rodent models have capably demonstrated quantifiable social and communicative behavioural traits, laying the ground for preclinical therapeutic studies.
As a caveat, it must be noted that a major limitation of ASD animal models relates to their inability to reflect heterogeneous environmental influences on the ASD phenotype, with various toxic, inflammatory and psychosocial factors difficult to incorporate in robust, reproducible animal models. This deficit in construct validity is especially relevant in modelling polygenic ASD, in which the gene × environment interaction plays a more fundamental role, and which therefore bears a particular risk for future translational work.
Locating and reversing ASD pathophysiology
Identifying specific cells and circuits dysregulated in ASD is crucial in gene therapy design, as vectors may be targeted to specific brain regions or cell types (discussed in detail later). In particular, nascent data suggest the hippocampus, cerebellum and corpus callosum contain key pathogenic circuits, whilst influential cell types include pyramidal cells, Purkinje cells and glial cells.
Recent technological advances have begun to elucidate the relationship between cell type-specific function and particular ASD endophenotypes. For example, in a RS mouse model, cre/lox-mediated deletion of MECP2 specifically from forebrain glutamatergic neurons led to a partial disease phenotype, with deficits in social behaviour and motor coordination, but preserved locomotor activity and fear-conditioned learning. Meanwhile, in a TSC mouse model, chemogenetic excitation of the Right Crus I (RCrusI) region of the cerebellum—an area consistently noted to be altered in the ASD brain in neuroanatomical and neuroimaging studies —was sufficient to specifically rescue social impairments, without rescuing repetitive or inflexible behaviours.
Within individual circuits, it appears that different ASD mutations may have opposing effects on synaptic function. For example, TSC2+/− and FMR1−/y knockouts appear to have opposite effects on mGluR-dependent long-term depression (LTD) in the hippocampus, whilst mice bred with both mutations balance each other out at the synaptic and behavioural levels. Such data not only exemplify the heterogeneic nature of ASD but also highlight the necessity of optimal synaptic control, and are the first hint that a successful gene therapy must walk a narrow therapeutic tightrope between over- and under-stimulating synaptic transmissions.
A crucial further question is whether autistic phenotypes can be reversed or are neurodevelopmentally fixed. Remarkably, an array of studies in different monogenic ASD animal models have consistently demonstrated the potential for reversal of established neuronal dysfunction, either after pharmacological intervention or genetic reactivation of silenced alleles. These findings imply that postnatally, indeed post-symptomatically, the genetic horse may not yet have bolted, and genetic correction via a delivered vector might be useful in treating cognitive dysfunction.
Delivering gene therapies to the CNS
If the ASD phenotype is reversible rather than neurodevelopmentally fixed, as implied by studies in monogenic animal models, then it follows that continuous genetic correction will be necessary for a sustained therapeutic effect. Currently, only viral packaging systems have combined efficient transduction with long-term gene expression in vivo (although, as will be discussed later, certain ASD conditions may be amenable to non-virally delivered antisense nucleic acid therapies).
Of the viruses which can transduce post-mitotic cells, rAAVs have emerged as the principal CNS delivery candidate. This is based upon their relatively low immunogenicity (compared to adenovirus and herpes simplex virus), limiting the likelihood of an encephalitic immune response, their ability to persist in episomal form, reducing their oncogenic potential (compared to retroviruses), and their high production titres. Indeed, rAAV vectors have already been used safely in a number of early clinical studies in CNS gene therapy, in disorders ranging from SMA to idiopathic Alzheimer’s disease.
Optimising cell-specific targeting is critical in maximising the number of transduced target cells/dose and limiting off-target toxicity. There are two major ways in which the spatial dynamics of rAAV vectors can be adjusted. Firstly, the properties of the vector itself can be modified, to include a cell type-selective capsid (e.g. AAV9 is particularly neurotropic) and/or promoter.
Secondly, the mode of delivery can be adjusted. Historically, rAAV vectors have been delivered intraparenchymally via stereotactic CNS injection, leading to high local concentrations with limited vector spread. Although invasive (each injection requiring a craniotomy), such a localising method of delivery might have utility in correcting specific dysregulated ASD circuits linked to particular clinical endophenotypes, analogous to the recent improvement in motor scores seen after lentiviral vector delivery of a dopamine-producing gene therapy to the nigrostriatal pathway in Parkinson’s disease.
However, ASD appears to involve global synaptic dysregulation and thus will require global CNS gene correction to fully reverse cognitive phenotypes. The discovery that rAAV9 crosses the blood-brain barrier (BBB) and globally transduces CNS neurons and glial cells, and the recent derivation of more efficient BBB-traversing rAAVs by targeted evolution, has opened up the possibility of using intravenous injection in ASD gene therapy.
It remains to be seen, however, whether side effects relating to peripheral tissue transduction, as well as the presence of neutralising circulating antibodies (anti-AAV9 antibodies are present in 47% of humans), will preclude intravenous administration in various ASDs. Changes to the viral vector nucleic acid sequence outside of the transgene—such as the inclusion of ‘detargeting’ sequences recognised by micro RNAs (miRNAs) expressed specifically in off-target cells —might circumvent the former issue, but use up highly limited space (rAAV’s packaging capacity is limited to ~ 5 kb). The latter issue may be negotiated by the use of engineered rAAV capsids, which may have lower neutralising antibody seropravalences.
An alternative to systemic delivery is intrathecal administration, which potentially combines (relatively) safe administration and global CNS transduction with fewer peripheral complications, and a higher spatial resolution limiting the dose requirements. However, there are conflicting data regarding the ability of intrathecally delivered rAAV to efficiently transduce areas outside the spinal cord, as well its own ability to avoid both peripheral leakage and a neutralising antibody response. Of note, an intrathecal AAV9 approach has been corrective in a model of giant axonal neuropathy and has progressed to a clinical trial.
Gene therapy strategies in monogenic ASD
Gene replacement
In ASD disorders defined by loss of function mutations (e.g. RS, FXS, TSC), simple gene replacement may restore synaptic function. Given the limitations imposed by imperfect gene delivery strategies, a key question is whether sufficient transduction of target cell types can be attained to exert phenotypic benefit.
Encouragingly, a number of studies using monogenic animal models have demonstrated behavioural improvements after rAAV-delivered gene replacement. In a RS mouse model, systemic delivery of a rAAV9-MECP2 vector sufficient for ~ 10% CNS transduction (of principally neuronal cells) led to moderate behavioural improvements. Meanwhile, at an ~ 6-fold higher vector dose, ~ 25% CNS transduction resulted in marked behavioural and phenotypic improvements. Finally, it was recently demonstrated that rAAV-mediated delivery of even a fragment of the MECP2 gene (lacking N- and C- terminal regions along with a central domain) led to phenotypic improvement in RS mice, potentially allowing extra room for construct modifications to aid target cell transduction and expression. Similarly, substantial phenotypic improvements were seen in studies using FXS and TSC models after intra-CNS delivery of replacement genes, although none of these studies quantified CNS transduction.
Although a cause for optimism, none of the above studies evidenced total phenotypic reversal after gene replacement. Such incomplete phenotypic reversal may be secondary to insufficient CNS transduction. In RS for example, ~ 80% gene reactivation in neuronal cells appears to be sufficient and necessary for total phenotypic reversal. However, increasing the vector dose in order to increase transduction must be balanced against the risk of dose-related toxicity. This may occur secondary to off-target cell transgene expression: for example, transgene-specific liver toxicity was seen at high doses of rAAV9-MECP2, possibly due to MECP2’s role in liver metabolism.
Toxicity may also occur secondary to supraphysiological expression in target cells. For example, after rAAV-mediated delivery of FMRP in FXS, toxicity developed at 2.5-fold expression above wild type, whilst duplication of MECP2 leads to MECP2 duplication syndrome in males. Such toxicity may occur even at low transduction percentages due to uneven vector distribution within the CNS or, in the case of X-linked disorders in females, due to a mosaic pattern of CNS expression caused by random X-inactivation. Reassuringly, a fragmented version of the MECP2 promoter appeared to limit MECP2 expression to physiological levels in both wild type and MECP2null/x female mice, even at vector doses leading to ~ 25% CNS transduction.
Nonetheless, further studies are required to pinpoint the optimum balance between CNS transduction and on-target toxicity in various ASD syndromes. Additionally, future gene replacement studies must better characterise the relationship between gene dose and dendritic function (which was not assessed in any of the above studies).
RNA knockdown
Gene expression can be silenced by sequence-specific knockdown of mRNA transcripts using techniques such as antisense oligonucleotides (ASOs) and short interfering RNAs (siRNAs), which use the exquisite specificity conferred by Watson-Crick base pairing to bind particular mRNA transcripts and prevent their translation (for a detailed mechanism see ref). These nucleic acids are typically relatively easy to manufacture, can be modified to limit degradation and inflammation, and do not require a viral vector (although long-term expression of ASOs is possible using viral delivery of short hairpin RNAs [shRNAs]). Indeed, such therapies are already being used in the treatment of SMA and in clinical trials for Huntington’s disease.
These techniques are principally useful when total or partial knockdown of a particular transcript may restore synaptic function. For example in MECP2 duplication syndrome, halving MECP2 expression was shown to restore cellular function and phenotype postnatally in a conditional MECP2-overexpressing mouse model. In the same study, intraventricular delivery of ASOs (delivered at a constant rate by a pump) specifically targeting MECP2 led to widespread ASO distribution in the CNS, effective knockdown of MECP2 to nearly wild type levels, and sustained phenotypic reversal (~ 10 weeks).
Another strategy in which RNA silencing may be useful is in knocking down a gene which inhibits a target gene’s expression, i.e. disinhibition. For example, triplication of 15q11-13 leads to a relatively common and highly penetrant type of autism linked to increased expression of UBE3A (which functions as a transcription regulator in addition to its ubiquitin ligase function) and subsequent downregulation of Cerebellin 1 Precursor (Cbln1), a synaptic organising protein, in the ventral tegmental area (VTA). Thus, knockdown of UBE3A could be used to restore sufficient Cbln1 expression in the VTA, which has already been shown to effect phenotypic change after cre/lox-mediated restoration in a UBE3A-triplicated mouse model.
Another application of this strategy could be in AS, where the long non-coding UBE3A antisense transcript (UBE3A-AST) causes imprinting of the paternal UBE3A allele, ensuring that a loss of maternal UBE3A allele function yields the AS phenotype (another example of how genetic defects in ASD may be bidirectional, with optimal gene expression in specific brain regions crucial). Indeed, a recent paper demonstrated that a single intracerebroventricular injection of a degradation-resistant ASO targeting UBE3A-AST in an adult AS mouse model led to specific and sustained reductions in UBE3A-AST levels, with partial restoration (~ 40%) of UBE3A levels throughout the CNS.
Interestingly, in the same study, whilst motor deficits were restored, other behaviours—such as anxiety and repetitive behaviours—were not. A later study, using Cre-dependent UBE3A reactivation in an AS mouse model, showed a temporal dependence for specific phenotype reversal, with anxiety and repetitive behaviours requiring gene reactivation during early development, whilst motor deficits could be restored into adulthood. Such temporal factors have not been thoroughly investigated in other monogenic ASDs but are clearly critical when considering the time point of useful intervention in humans.
Finally, in a similar vein to excessive gene replacement, hyper-knockdown of target RNA may lead to rebound toxicity in both target cells and off-target cells. Furthermore, both ASOs and siRNA may cause unpredictable off-target knockdown. From this perspective, the requirement for regular intra-CNS administration of ASOs is a double-edged sword in ASD: whilst on the one hand, it is clearly less convenient than a once-off injection of viral vector, on the other hand, it allows for the possibility of dose uptitration and determination of an optimal therapeutic level.
Gene editing
One of the most exciting recent developments in gene therapy is the advent of easily customised sequence-specific editing techniques, such as CRISPR (clustered regularly interspaced short palindromic repeats)-Cas9, enabling either correction of a genetic mutation via non-homologous recombination (providing there is a suitable template) or gene silencing via non-homologous end-joining. Such techniques would generally enable gene expression at physiological levels in target cells, negating the problems of transgene-associated toxicity seen with both gene replacement and RNA knockdown techniques.
Unfortunately, at least in vivo, gene editing techniques still remain a distant therapeutic prospect, with a wealth of technical hurdles to overcome, including how to deliver gene editing systems to target cells, how to increase the efficiency of editing, and how to avoid off-target editing. Still, recent work by Doudna and colleagues provides optimism in this regard, with the demonstration of greatly improved editing of post-mitotic neurons in adult mouse brains using cell-penetrating peptides tagged onto Cas9 ribonucleoprotein complexes.
Prospects for gene therapy in polygenic ASD
As previously mentioned, in comparison with monogenic ASD, polygenic ASD has a greater environmental component driving its phenotype. In this respect, damaging, nonsynonymous postzygotic mutations in whole-exome sequences from the largest collection of trios with ASD were recently identified, with some of these genes being particularly enriched for expression in the amygdala, a key brain region for social conditioning and learning. Such factors, combined with the current paucity and constructional limitations of animal models in polygenic ASD, make it a less obvious target for gene therapy.
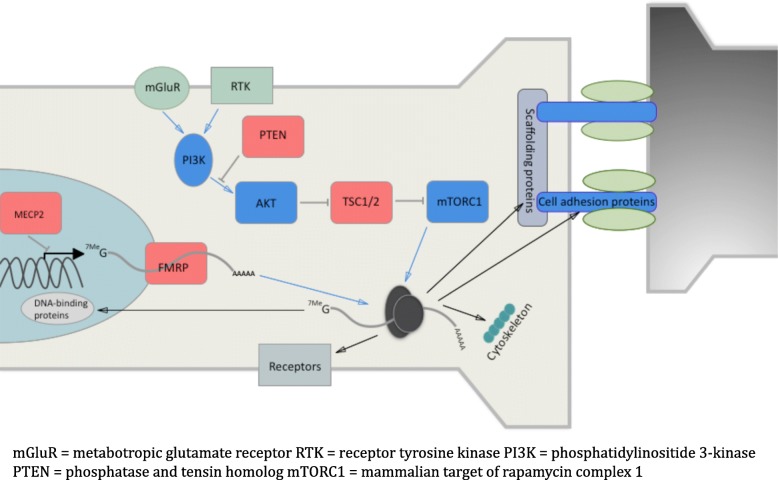
Nonetheless, despite the bewildering array of rare genetic mutations linked to polygenic ASD, an important focus of these mutations appears to be in the regulation of synaptic function, with diverse ASD mutations potentially connecting aberrant translational inputs and outputs (Fig. 1). For example, in mice, deletion of the translational repressor Eukaryotic translation initiation factor 4E-binding protein 2 (4E-BP2) led to overexpression of the NLGN class of cell adhesion molecules, mutations of which have been causally linked to ASD. Furthermore, such deletion resulted in disruption of the ratio of excitatory to inhibitory synaptic inputs, as well as an ASD behavioural phenotype, which was corrected by NLGN1 knockdown.
This leads to the idea that many ASD mutations might be treated by fine-tuning the expression of influential proteins acting within dynamic translational loops. The apparently fundamental role of the PI3K-AKT-mTOR pathway in various causes of monogenic ASD, as well as the phenotypic reversal seen using small molecule inhibitors of mTORC1 preclinically, suggests that this pathway may be a critical target for gene therapy in certain cases of ASD.
However, given ASD’s heterogeneity, it is once again important not to focus myopically on a single pathway. Rather, instead of embarking on a ‘one size fits all’ therapeutic approach, the effect of any particular ASD mutation on translational output and synaptic function should be categorised, before deciding whether and how to target a particular gene or pathway. For instance, NLGN3 knockout mice demonstrate a FXS-like disruption of mGluR-dependent synaptic plasticity, suggesting that either FMRP overexpression or PI3K-AKT-mTOR pathway knockdown (given the aforementioned opposition of these two pathways) might correct this phenotype.
Finally, recent evidence has emerged of ASD behaviours caused by amino acid deficits. For example, homozygous dysfunction of the BBB solute carrier transporter 7a5 (SLC7A5) and corresponding CNS loss of branched chain amino acids (BCAAs) has been linked to ASD, which is reversible in mouse models upon intra-CNS administration of BCAAs. Thus, direct protein replacement therapy might provide an important additional therapeutic avenue in certain ASD cases. It is also possible to imagine using gene therapy as an adjunct here: for example, combining systemic BCAA replacement with vector-delivered SLC7A5 targeting BBB cells.
Conclusions
Given the heritable component of ASD, gene therapy offers a promising alternative to conventional small molecule therapies. Preclinical studies over the last 5 years using animal models displaying autism-like traits have demonstrated that directly altering gene expression using rAAV-delivered transgenes can reverse the behavioural phenotype, either via gene replacement or RNA knockdown. Such studies establish proof-of-concept and set up a platform for clinical translation in various monogenic ASDs, with RS being a frontrunner in this regard.
However, major hurdles remain, not least the fact that the majority of ASD disorders, even monogenic ones, show variable penetrance, with epistatic and gene × environment interactions determining phenotype. Not only is such genetic and environmental heterogeneity inherently difficult to model, hindering clinical translation, but also in clinical trials that do go ahead, ASD subgroups that benefit from a particular treatment may be lost amongst other unsuitable subgroups. Furthermore, we still do not know whether, or in which cases, epigenetic factors may preclude reversibility in humans. Cyclically, this brings us back to the question of animal models and whether these have sufficient construct validity to actually begin to answer such questions in the first place.
A number of additional questions remain: Firstly, can vector design be optimised to the extent that intravenous delivery achieves sufficient CNS transduction without peripheral toxicity? Secondly, where is the optimum balance between CNS transduction and the risk of on-target transgene-related toxicity for each ASD syndrome? Thirdly, will demonstrations of acceptable levels of CNS toxicity hold when studies commence in larger animal models? Fourthly, is there a time point beyond which some or all autistic features lose their reversibility? Answering these questions will be key to moving ASD gene therapy into clinical trials, and perhaps one day generating a genetic treatment for ASD.
Sources
- Christensen DL, et al. Prevalence of autism spectrum disorder among children aged 8 years—autism and developmental disabilities monitoring network, 11 sites, United States, 2010.,” Morb. Mortal. Wkly. Rep. Surveill. Summ. Wash. DC 2002, vol. 63, no. 2, pp. 1–21, Mar. 2014. https://pubmed.ncbi.nlm.nih.gov/24670961/
- Chahrour M, O’Roak BJ, Santini E, Samaco RC, Kleiman RJ, Manzini MCCurrent perspectives in autism disorder: from genes to therapyJ. Neurosci2016364511402 https://doi.org/10.1523/JNEUROSCI.2335-16.2016
- Zafeiriou DI, Ververi A, Vargiami E. Childhood autism and associated comorbidities. Brain Dev. 29(5):257–72. https://doi.org/10.1016/j.braindev.2006.09.003
- Buescher AVS, Cidav Z, Knapp M, Mandell DSCosts of autism spectrum disorders in the United Kingdom and the United StatesJAMA Pediatr20141688721728 https://doi.org/10.1001/jamapediatrics.2014.210
- LeClerc S, Easley DPharmacological therapies for autism spectrum disorder: a reviewPharm Ther2015406389397 https://pubmed.ncbi.nlm.nih.gov/26045648/
- Freitag CMThe genetics of autistic disorders and its clinical relevance: a review of the literatureMol Psychiatry2006121222 https://doi.org/10.1038/sj.mp.4001896
- Geschwind DH, State MWGene hunting in autism spectrum disorder: on the path to precision medicineLancet Neurol2015141111091120 https://doi.org/10.1016/S1474-4422(15)00044-7
- Careaga M, Murai T, Bauman MDMaternal immune activation and autism spectrum disorder: from rodents to nonhuman and human primatesBiol Psychiatry2017815391401 https://doi.org/10.1016/j.biopsych.2016.10.020
- Modabbernia A, Velthorst E, Reichenberg AEnvironmental risk factors for autism: an evidence-based review of systematic reviews and meta-analysesMol. Autism20178113 https://doi.org/10.1186/s13229-017-0121-4
- Tordjman SGene × Environment interactions in autism spectrum disorders: role of epigenetic mechanismsFront Psychiatry2014553 https://doi.org/10.3389/fpsyt.2014.00053
- Hopkins AL, Groom CRThe druggable genomeNat Rev Drug Discov200219727730 https://doi.org/10.1038/nrd892
- Templeton NS. Gene and cell therapy: therapeutic mechanisms and strategies. 4th ed: CRC Press; 2015, Boca Raton, FL.
- Naldini LGene therapy returns to centre stageNature20155267573351360 https://doi.org/10.1038/nature15818
- Hoy SMNusinersen: first global approvalDrugs2017774473479 https://doi.org/10.1007/s40265-017-0711-7
- Shaberman BA retinal research nonprofit paves the way for commercializing gene therapiesHum Gene Ther2017281211181121 https://doi.org/10.1089/hum.2017.29058.bsh
- Mendell JRSingle-dose gene-replacement therapy for spinal muscular atrophyN Engl J Med20173771817131722 https://doi.org/10.1056/NEJMoa1706198
- Hampson G, Towse A, Pearson SD, Dreitlein WB, Henshall CGene therapy: evidence, value and affordability in the US health care systemJ Comp Eff Res2018711528 https://doi.org/10.2217/cer-2017-0068
- Sztainberg Y, Zoghbi HYLessons learned from studying syndromic autism spectrum disordersNat Neurosci2016191114081417 https://doi.org/10.1038/nn.4420
- Amir RE, Van den Veyver IB, Wan M, Tran CQ, Francke U, Zoghbi HYRett syndrome is caused by mutations in X-linked MECP2, encoding methyl-CpG-binding protein 2Nat Genet1999232185188 https://doi.org/10.1038/13810
- Kishino T, Lalande M, Wagstaff JUBE3A/E6-AP mutations cause Angelman syndromeNat Genet19971517073 https://doi.org/10.1038/ng0197-70
- Splawski I, et al. CaV1.2 calcium channel dysfunction causes a multisystem disorder including arrhythmia and autism. Cell. 119(1):19–31. https://doi.org/10.1016/j.cell.2004.09.011
- van Slegtenhorst MIdentification of the tuberous sclerosis gene TSC1 on chromosome 9q34Science19972775327805808 https://doi.org/10.1126/science.277.5327.805
- Verkerk AJIdentification of a gene (FMR-1) containing a CGG repeat coincident with a breakpoint cluster region exhibiting length variation in fragile X syndromeCell1991655905914 https://doi.org/10.1016/0092-8674(91)90397-H
- Yuen RKCWhole genome sequencing resource identifies 18 new candidate genes for autism spectrum disorderNat Neurosci2017204602611 https://doi.org/10.1038/nn.4524
- De Rubeis SSynaptic, transcriptional and chromatin genes disrupted in autismNature20145157526209215 https://doi.org/10.1038/nature13772
- Iossifov IThe contribution of de novo coding mutations to autism spectrum disorderNature20145157526216221 https://doi.org/10.1038/nature13908
- Iossifov IDe novo gene disruptions in children on the autistic spectrumNeuron2012742285299 https://doi.org/10.1016/j.neuron.2012.04.009
- Jiang YDetection of clinically relevant genetic variants in autism spectrum disorder by whole-genome sequencingAm J Hum Genet2013932249263 https://doi.org/10.1016/j.ajhg.2013.06.012
- Neale BMPatterns and rates of exonic de novo mutations in autism spectrum disordersNature20124857397242245 https://doi.org/10.1038/nature11011
- O’Roak BJExome sequencing in sporadic autism spectrum disorders identifies severe de novo mutationsNat Genet2011436585589 https://doi.org/10.1038/ng.835
- Sanders SJDe novo mutations revealed by whole-exome sequencing are strongly associated with autismNature20124857397237241 https://doi.org/10.1038/nature10945
- Yuen RKCWhole-genome sequencing of quartet families with autism spectrum disorderNat Med2015212185191 https://doi.org/10.1038/nm.3792
- Zoghbi HY, Bear MF. Synaptic dysfunction in neurodevelopmental disorders associated with autism and intellectual disabilities. Cold Spring Harb. Perspect. Biol. 2012;4(3) https://doi.org/10.1101/cshperspect.a009886
- Kleijer KTENeurobiology of autism gene products: towards pathogenesis and drug targetsPsychopharmacology2014231610371062 https://doi.org/10.1007/s00213-013-3403-3
- Loke YJ, Hannan AJ, Craig JMThe role of epigenetic change in autism spectrum disordersFront Neurol20156107 https://doi.org/10.3389/fneur.2015.00107
- Onore C, Careaga M, Ashwood PThe role of immune dysfunction in the pathophysiology of autismBrain Behav Immun2012263383392 https://doi.org/10.1016/j.bbi.2011.08.007
- Beversdorf DQ, MISSOURI AUTISM SUMMIT CONSORTIUMPhenotyping, etiological factors, and biomarkers: toward precision medicine in autism spectrum disordersJ Dev Behav Pediatr2016378659673 https://doi.org/10.1097/DBP.0000000000000351
- Berry-Kravis EMEffects of STX209 (arbaclofen) on neurobehavioral function in children and adults with fragile X syndrome: a randomized, controlled, phase 2 trialSci. Transl. Med20124152152ra127 https://doi.org/10.1126/scitranslmed.3004214
- Denayer T, Stöhr T, Van Roy MAnimal models in translational medicine: validation and predictionNew Horiz Transl Med201421511
- Huerta M, Lord CDiagnostic evaluation of autism spectrum disordersPediatr Clin N Am2012591103111 https://doi.org/10.1016/j.pcl.2011.10.018
- Bekoff MAnimal Emotions: Exploring Passionate Natures: current interdisciplinary research provides compelling evidence that many animals experience such emotions as joy, fear, love, despair, and grief—we are not aloneBioScience20005010861870 https://doi.org/10.1641/0006-3568(2000)050[0861:AEEPN]2.0.CO;2
- Stafstrom CE, Benke TAAutism and epilepsy: exploring the relationship using experimental modelsEpilepsy Curr2015154206210 https://doi.org/10.5698/1535-7511-15.4.206
- Crawley JNTranslational animal models of autism and neurodevelopmental disordersDialogues Clin Neurosci2012143293305 https://doi.org/10.31887/DCNS.2012.14.3/jcrawley
- Hulbert SW, Jiang YMonogenic mouse models of autism spectrum disorders: common mechanisms and missing linksNeuroscience2016321323 https://doi.org/10.1016/j.neuroscience.2015.12.040
- Persico AM, Napolioni VAutism geneticsBehav Brain Res201325195112 https://doi.org/10.1016/j.bbr.2013.06.012
- Kim H, Lim C-S, Kaang B-KNeuronal mechanisms and circuits underlying repetitive behaviors in mouse models of autism spectrum disorderBehav. Brain Funct20161213 https://doi.org/10.1186/s12993-016-0087-y
- D’Mello AM, Stoodley CJCerebro-cerebellar circuits in autism spectrum disorderFront Neurosci20159408 https://doi.org/10.3389/fnins.2015.00408
- Li JIntegrated systems analysis reveals a molecular network underlying autism spectrum disordersMol. Syst. Biol20141012774 https://doi.org/10.15252/msb.20145487
- Petrelli F, Pucci L, Bezzi PAstrocytes and microglia and their potential link with autism spectrum disordersFront Cell Neurosci20161021 https://doi.org/10.3389/fncel.2016.00021
- Gemelli T, Berton O, Nelson ED, Perrotti LI, Jaenisch R, Monteggia LMPostnatal loss of methyl-CpG binding protein 2 in the forebrain is sufficient to mediate behavioral aspects of Rett syndrome in miceBiol Psychiatry2006595468476 https://doi.org/10.1016/j.biopsych.2005.07.025
- Skefos JRegional alterations in purkinje ell density in patients with autismPLoS ONE201492e81255 https://doi.org/10.1371/journal.pone.0081255
- D’Mello AM, Crocetti D, Mostofsky SH, Stoodley CJCerebellar gray matter and lobular volumes correlate with core autism symptomsNeuroImage Clin20157631639 https://doi.org/10.1016/j.nicl.2015.02.007
- Stoodley CJAltered cerebellar connectivity in autism and cerebellar-mediated rescue of autism-related behaviors in miceNat Neurosci2017201217441751 https://doi.org/10.1038/s41593-017-0004-1
- Auerbach BD, Osterweil EK, Bear MFMutations causing syndromic autism define an axis of synaptic pathophysiologyNature201148073756368 https://doi.org/10.1038/nature10658
- Dolen GCorrection of fragile X syndrome in miceNeuron2007566955962 https://doi.org/10.1016/j.neuron.2007.12.001
- Guy J, Gan J, Selfridge J, Cobb S, Bird AReversal of neurological defects in a mouse model of Rett syndromeScience2007315581511431147 https://doi.org/10.1126/science.1138389
- Ehninger DReversal of learning deficits in a Tsc2+/− mouse model of tuberous sclerosisNat Med2008148843848 https://doi.org/10.1038/nm1788
- Dolan BMRescue of fragile X syndrome phenotypes in Fmr1 KO mice by the small-molecule PAK inhibitor FRAX486Proc Natl Acad Sci U S A20131101456715676 https://doi.org/10.1073/pnas.1219383110
- Sztainberg YReversal of phenotypes in MECP2 duplication mice using genetic rescue or antisense oligonucleotidesNature20155287580123126 https://doi.org/10.1038/nature16159
- Mei YAdult restoration of Shank3 expression rescues selective autistic-like phenotypesNature20165307591481484 https://doi.org/10.1038/nature16971
- Choudhury SR, Hudry E, Maguire CA, Sena-Esteves M, Breakefield XO, Grandi PViral vectors for therapy of neurologic diseasesSmall Mol. Neurol. Disord2017120Supplement C6380 https://doi.org/10.1016/j.neuropharm.2016.02.013
- Gray SJGene therapy and neurodevelopmental disordersNeurodev. Disord201368Supplement C136142 https://doi.org/10.1016/j.neuropharm.2012.06.024
- Modlich U, et al. Insertional transformation of hematopoietic cells by self-inactivating lentiviral and gammaretroviral vectors. Mol. Ther. 1919–1928;17(11) https://doi.org/10.1038/mt.2009.179
- Hacein-Bey-Abina SInsertional oncogenesis in 4 patients after retrovirus-mediated gene therapy of SCID-X1J Clin Invest2008118931323142 https://doi.org/10.1172/JCI35700
- Hocquemiller M, Giersch L, Audrain M, Parker S, Cartier NAdeno-associated virus-based gene therapy for CNS diseasesHum Gene Ther2016277478496 https://doi.org/10.1089/hum.2016.087
- Taymans J-MComparative analysis of adeno-associated viral vector serotypes 1, 2, 5, 7, and 8 in mouse brainHum Gene Ther2007183195206 https://doi.org/10.1089/hum.2006.178
- Aschauer DF, Kreuz S, Rumpel SAnalysis of transduction efficiency, tropism and axonal transport of AAV serotypes 1, 2, 5, 6, 8 and 9 in the mouse brainPLOS ONE201389e76310 https://doi.org/10.1371/journal.pone.0076310
- Powell SK, Rivera-Soto R, Gray SJViral expression cassette elements to enhance transgene target specificity and expression in gene therapyDiscov Med2015191024957 https://pubmed.ncbi.nlm.nih.gov/25636961/
- Vite CH, Passini MA, Haskins ME, Wolfe JHAdeno-associated virus vector-mediated transduction in the cat brainGene Ther2003102218741881 https://doi.org/10.1038/sj.gt.3302087
- S. Palfi et al., “Long-term safety and tolerability of ProSavin, a lentiviral vector-based gene therapy for Parkinson’s disease: a dose escalation, open-label, phase 1/2 trial,” The Lancet, 383, 9923, 1138–1146. 2014 https://doi.org/10.1016/S0140-6736(13)61939-X
- Katz DM, et al. Rett syndrome: crossing the threshold to clinical translation. Trends Neurosci. 39(2):100–13. https://doi.org/10.1016/j.tins.2015.12.008
- Bruno JL, Hosseini SMH, Saggar M, Quintin E-M, Raman MM, Reiss ALAltered brain network segregation in fragile X syndrome revealed by structural connectomicsCereb Cortex201727322492259 https://doi.org/10.1093/cercor/bhw055
- Dehay B, Dalkara D, Dovero S, Li Q, Bezard E. Systemic scAAV9 variant mediates brain transduction in newborn rhesus macaques. 2012;2:253. https://doi.org/10.1038/srep00253
- Deverman BECre-dependent selection yields AAV variants for widespread gene transfer to the adult brainNat Biotech2016342204209 https://doi.org/10.1038/nbt.3440
- Boutin SPrevalence of serum IgG and neutralizing factors against adeno-associated virus (AAV) types 1, 2, 5, 6, 8, and 9 in the healthy population: implications for gene therapy using AAV vectorsHum Gene Ther2010216704712 https://doi.org/10.1089/hum.2009.182
- Gray SJ, Matagne V, Bachaboina L, Yadav S, Ojeda SR, Samulski RJ. Preclinical differences of intravascular AAV9 delivery to neurons and glia: a comparative study of adult mice and nonhuman primates. Mol. Ther. 19(6):1058–69. https://doi.org/10.1038/mt.2011.72
- Mingozzi F, High KAImmune responses to AAV vectors: overcoming barriers to successful gene therapyBlood201312212336 https://doi.org/10.1182/blood-2013-01-306647
- Geisler A, Fechner HMicroRNA-regulated viral vectors for gene therapyWorld J Exp Med2016623754 https://doi.org/10.5493/wjem.v6.i2.37
- Grieger JC, Samulski RJPackaging capacity of adeno-associated virus serotypes: impact of larger genomes on infectivity and postentry stepsJ Virol2005791599339944 https://doi.org/10.1128/JVI.79.15.9933-9944.2005
- Tse LVStructure-guided evolution of antigenically distinct adeno-associated virus variants for immune evasionProc Natl Acad Sci201711424E4812E4821 https://doi.org/10.1073/pnas.1704766114
- Federici TRobust spinal motor neuron transduction following intrathecal delivery of AAV9 in pigsGene Ther2012198852859 https://doi.org/10.1038/gt.2011.130
- Schuster DJBiodistribution of adeno-associated virus serotype 9 (AAV9) vector after intrathecal and intravenous delivery in mouseFront Neuroanat2014842 https://doi.org/10.3389/fnana.2014.00042
- Samaranch LAdeno-associated virus serotype 9 transduction in the central nervous system of nonhuman primatesHum Gene Ther2012234382389 https://doi.org/10.1089/hum.2011.200
- Saraiva J, Nobre RJ, Pereira de Almeida LGene therapy for the CNS using AAVs: the impact of systemic delivery by AAV9J. Controlled Release2016241Supplement C94109 https://doi.org/10.1016/j.jconrel.2016.09.011
- Mussche SRestoration of cytoskeleton homeostasis after gigaxonin gene transfer for giant axonal neuropathyHum Gene Ther2013242209219 https://doi.org/10.1089/hum.2012.107
- Gadalla KKImproved survival and reduced phenotypic severity following AAV9/MECP2 gene transfer to neonatal and juvenile male Mecp2 knockout miceMol Ther20132111830 https://doi.org/10.1038/mt.2012.200
- Matagne VA codon-optimized Mecp2 transgene corrects breathing deficits and improves survival in a mouse model of Rett syndromeNeurobiol Dis201799111 https://doi.org/10.1016/j.nbd.2016.12.009
- Garg SKSystemic delivery of MeCP2 rescues behavioral and cellular deficits in female mouse models of Rett syndromeJ. Neurosci2013333413612 https://doi.org/10.1523/JNEUROSCI.1854-13.2013
- Tillotson RRadically truncated MeCP2 rescues Rett syndrome-like neurological defectsNature2017550398 https://doi.org/10.1038/nature24058
- Zeier Z, Kumar A, Bodhinathan K, Feller JA, Foster TC, Bloom DCFragile X mental retardation protein replacement restores hippocampal synaptic function in a mouse model of fragile X syndromeGene Ther200916911221129 https://doi.org/10.1038/gt.2009.83
- Gholizadeh S, Arsenault J, Xuan ICY, Pacey LK, Hampson DRReduced phenotypic severity following adeno-associated virus-mediated Fmr1 gene delivery in fragile X miceNeuropsychopharmacol Off Publ Am Coll Neuropsychopharmacol2014391331003111 https://doi.org/10.1038/npp.2014.167
- Prabhakar SSurvival benefit and phenotypic improvement by hamartin gene therapy in a tuberous sclerosis mouse brain modelNeurobiol Dis2015822231 https://doi.org/10.1016/j.nbd.2015.04.018
- Robinson LMorphological and functional reversal of phenotypes in a mouse model of Rett syndromeBrain2012135926992710 https://doi.org/10.1093/brain/aws096
- Gadalla KKDevelopment of a novel AAV gene therapy cassette with improved safety features and efficacy in a mouse model of Rett syndromeMol Ther Methods Clin Dev20175180190 https://doi.org/10.1016/j.omtm.2017.04.007
- Kyle SM, Saha PK, Brown HM, Chan LC, Justice MJMeCP2 co-ordinates liver lipid metabolism with the NCoR1/HDAC3 corepressor complexHum Mol Genet2016251430293041 https://doi.org/10.1093/hmg/ddw156
- Arsenault JFMRP expression levels in mouse central nervous system neurons determine behavioral phenotypeHum Gene Ther20162712982996 https://doi.org/10.1089/hum.2016.090
- Friez MJRecurrent infections, hypotonia, and mental retardation caused by duplication of MECP2 and adjacent region in Xq28Pediatrics20061186e1687 https://doi.org/10.1542/peds.2006-0395
- Meins MSubmicroscopic duplication in Xq28 causes increased expression of the MECP2 gene in a boy with severe mental retardation and features of Rett syndromeJ Med Genet2005422e12 https://doi.org/10.1136/jmg.2004.023804
- Van Esch HDuplication of the MECP2 region is a frequent cause of severe mental retardation and progressive neurological symptoms in malesAm J Hum Genet2005773442453 https://doi.org/10.1086/444549
- Lyon MFX-chromosome inactivation and human genetic diseaseActa Paediatr Oslo Nor 1992 Suppl200291439107112 https://doi.org/10.1111/j.1651-2227.2002.tb03120.x
- Kole R, Krainer AR, Altman SRNA therapeutics: beyond RNA interference and antisense oligonucleotidesNat Rev Drug Discov2012112125140 https://doi.org/10.1038/nrd3625
- Wittrup A, Lieberman JKnocking down disease: a progress report on siRNA therapeuticsNat Rev Genet2015169543552 https://doi.org/10.1038/nrg3978
- Scoto M, Finkel RS, Mercuri E, Muntoni FTherapeutic approaches for spinal muscular atrophy (SMA)Gene Ther2017249514519 https://doi.org/10.1038/gt.2017.45
- Wild EJ, Tabrizi SJ. Therapies targeting DNA and RNA in Huntington’s disease. Lancet Neurol. 16, 10:837–47. https://doi.org/10.1016/S1474-4422(17)30280-6
- Sztainberg YReversal of phenotypes in MECP2 duplication mice using genetic rescue or antisense oligosNature20155287580123126 https://doi.org/10.1038/nature16159
- Krishnan VAutism gene Ube3a and seizures impair sociability by repressing VTA Cbln1Nature20175437646507512 https://doi.org/10.1038/nature21678
- Meng L, Ward AJ, Chun S, Bennett CF, Beaudet AL, Rigo FTowards a therapy for Angelman syndrome by reduction of a long non-coding RNANature20155187539409412 https://doi.org/10.1038/nature13975
- Silva-Santos SUbe3a reinstatement identifies distinct developmental windows in a murine Angelman syndrome modelJ Clin Invest2015125520692076 https://doi.org/10.1172/JCI80554
- Watts JK, Corey DRGene silencing by siRNAs and antisense oligonucleotides in the laboratory and the clinicJ Pathol20122262365379 https://doi.org/10.1002/path.2993
- Maeder ML, Gersbach CAGenome-editing technologies for gene and cell therapyMol Ther2016243430446 https://doi.org/10.1038/mt.2016.10
- Peng R, Lin G, Li JPotential pitfalls of CRISPR/Cas9-mediated genome editingFEBS J2016283712181231 https://doi.org/10.1111/febs.13586
- Wang LIn vivo delivery systems for therapeutic genome editingInt J Mol Sci2016175626 https://doi.org/10.3390/ijms17050626
- Staahl BTEfficient genome editing in the mouse brain by local delivery of engineered Cas9 ribonucleoprotein complexesNat Biotech2017355431434 https://doi.org/10.1038/nbt.3806
- Lim ETRates, distribution and implications of postzygotic mosaic mutations in autism spectrum disorderNat Neurosci2017201217 https://doi.org/10.1038/nn.4598
- Gkogkas CGAutism-related deficits via dysregulated eIF4E-dependent translational controlNature20134937432371377 https://doi.org/10.1038/nature11628
- Südhof TCNeuroligins and neurexins link synaptic function to cognitive diseaseNature20084557215903911 https://doi.org/10.1038/nature07456
- Singh SK, Eroglu CNeuroligins provide molecular links between syndromic and nonsyndromic autismSci Signal20136283re4 https://doi.org/10.1126/scisignal.2004102
- Sato AmTOR, a potential target to treat autism spectrum disorderCNS Neurol Disord Drug Targets2016155533543 https://doi.org/10.2174/1871527315666160413120638
- Sato A, et al. “Rapamycin reverses impaired social interaction in mouse models of tuberous sclerosis complex,” Nat Commun. 2012;3:1292. https://doi.org/10.1038/ncomms2295
- Baudouin SJShared synaptic pathophysiology in syndromic and nonsyndromic rodent models of autismScience20123386103128132 https://doi.org/10.1126/science.1224159
- Novarino GMutations in BCKD-kinase lead to a potentially treatable form of autism with epilepsyScience20123386105394397 https://doi.org/10.1126/science.1224631
- Tarlungeanu DCImpaired amino acid transport at the blood brain barrier is a cause of autism spectrum disorderCell2016167614811494.e18 https://doi.org/10.1016/j.cell.2016.11.013
- Sethna F, Moon C, Wang HFrom FMRP function to potential therapies for fragile X syndromeNeurochem Res201439610161031 https://doi.org/10.1007/s11064-013-1229-3
- Richards C, Jones C, Groves L, Moss J, Oliver CPrevalence of autism spectrum disorder phenomenology in genetic disorders: a systematic review and meta-analysisLancet Psychiatry2015210909916 https://doi.org/10.1016/S2215-0366(15)00376-4
- Guy J, Cheval H, Selfridge J, Bird AThe role of MeCP2 in the brainAnnu Rev Cell Dev Biol2011271631652 https://doi.org/10.1146/annurev-cellbio-092910-154121
- Ramocki MBAutism and other neuropsychiatric symptoms are prevalent in individuals with MECP2 duplication syndromeAnn Neurol2009666771782 https://doi.org/10.1002/ana.21715
- Tee AR, Fingar DC, Manning BD, Kwiatkowski DJ, Cantley LC, Blenis JTuberous sclerosis complex-1 and -2 gene products function together to inhibit mammalian target of rapamycin (mTOR)-mediated downstream signalingProc Natl Acad Sci200299211357113576 https://doi.org/10.1073/pnas.202476899
- Tomaic V, Banks LAngelman syndrome-associated ubiquitin ligase UBE3A/E6AP mutants interfere with the proteolytic activity of the proteasomeCell Death Dis20156e1625 https://doi.org/10.1038/cddis.2014.572
- Betancur C, Sakurai T, Buxbaum JD. The emerging role of synaptic cell-adhesion pathways in the pathogenesis of autism spectrum disorders. Trends Neurosci. 32(7):402–12. https://doi.org/10.1016/j.tins.2009.04.003
- Ye H, Liu J, Wu JYCell adhesion molecules and their involvement in autism spectrum disorderNeurosignals20101826271 https://doi.org/10.1159/000322543
- Ting JT, Peça J, Feng GFunctional consequences of mutations in postsynaptic scaffolding proteins and relevance to psychiatric disordersAnnu Rev Neurosci20123514971 https://doi.org/10.1146/annurev-neuro-062111-150442
- Zheng FEvidence for association between Disrupted-in-schizophrenia 1 (DISC1) gene polymorphisms and autism in Chinese Han population: a family-based association studyBehav. Brain Funct20117114 https://doi.org/10.1186/1744-9081-7-14
- Chen J, Yu S, Fu Y, Li XSynaptic proteins and receptors defects in autism spectrum disordersFront Cell Neurosci20148276 https://doi.org/10.3389/fncel.2014.00276
- Rojas DCThe role of glutamate and its receptors in autism and the use of glutamate receptor antagonists in treatmentJ Neural Transm Vienna Austria 199620141218891905 https://doi.org/10.1007/s00702-014-1216-0
- Platt RJ, et al. Chd8 mutation leads to autistic-like behaviors and impaired striatal circuits. Cell Rep. 19(2):335–50. https://doi.org/10.1016/j.celrep.2017.03.052
- Breuss MW, Gleeson JGWhen size matters: CHD8 in autismNat Neurosci2016191114301432 https://doi.org/10.1038/nn.4431